
ISSA Healthcare Insider Newsletter
Insights, resources, and opportunities shaping the future of healthcare environmental hygiene.
Biofilm: The Invisible Barrier to a Clean Healthcare Environment
August 21, 2026
Biofilm is something you cannot see, but it quietly shapes how well healthcare environments can be cleaned and disinfected. On a microscope slide, it looks like a dense, slimy community of microbes glued together; on real-world surfaces, it is an invisible barrier that can protect pathogens from the very products intended to remove them. Understanding how biofilm forms, and how modern healthcare surfaces help it persist, is essential if the goal is truly clean, safe environments of care.
How biofilm forms on surfaces
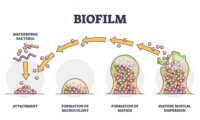 Most microbes in nature do not live as free-floating single cells. They prefer to attach to surfaces and form structured communities encased in a self-produced matrix of extracellular polymeric substances (EPS)—a mix of polysaccharides, proteins, lipids, and extracellular DNA. The process typically starts when planktonic (free) cells encounter a surface. Weak, reversible attachment is followed by stronger, irreversible adhesion as cells produce adhesins and begin to secrete matrix material.
Once attached, the microbes multiply and organize into microcolonies. These colonies grow into mature, three-dimensional biofilms with channels that allow nutrients and waste to move through the structure. Within this matrix, cells change their gene expression, slow their growth rate, and coordinate behavior through quorum sensing. The final stage is dispersion: some cells escape the matrix and return to a free-floating state, ready to colonize new surfaces. This continual cycle is one reason environmental contamination can reappear even after cleaning.
Why biofilm resists cleaning and disinfection
 From a microbiology perspective, biofilm is a highly effective survival strategy. In healthcare settings, it has major implications for cleaning and disinfection. Surface-attached cells and biofilms are significantly less susceptible to biocides, antibiotics, and physical stress than their free-floating counterparts. The EPS matrix acts like a physical and chemical shield, slowing the penetration of disinfectants and binding or neutralizing active ingredients before they reach cells deep in the biofilm.
The organisms inside a biofilm are also physiologically different. Many grow more slowly and may enter a stress-tolerant state, making them inherently less affected by agents that target rapidly dividing cells. On top of that, biofilms on environmental surfaces are often mixed communities. Different species can protect one another, share resistance genes, and create microenvironments that further reduce the impact of cleaning and disinfectant products.
For the healthcare cleaning team, the result is discouraging but important: a surface can look visually clean and still harbor a well-established biofilm that survives routine cleaning and disinfection cycles. This helps explain how vegetative bacteria can persist for weeks or months on hospital surfaces and why organisms may not be evenly recovered during environmental sampling.
Dry, “clean” healthcare surfaces and biofilm
Biofilm is often associated with wet environments—drains, tubing, and indwelling devices—but research now shows that biofilms can also form on apparently dry hospital surfaces. Microbes can survive in a desiccated state in dust, organic residues, and micro-environments on surfaces, then take advantage of intermittent moisture from cleaning processes, spills, or human touch to grow and rebuild their matrix.
Healthcare surfaces themselves can unintentionally support attachment and biofilm formation. Many common materials have microscopic scratches, pores, or seams that create protected niches where moisture and soil accumulate and where disinfectants do not fully reach. Surface energy, texture, and chemistry can increase microbial adhesion, especially when combined with the organic load (body fluids, skin cells, product residues) that inevitably builds up in real clinical environments.
Repeated cleaning with detergents that remove loose soil but do not disrupt the biofilm matrix can actually leave a “conditioned” surface behind—a thin layer of organic material that improves microbial attachment the next time organisms land there. Over time, this can allow dry-surface biofilms to become a persistent source of contamination in patient rooms, high-touch areas, and equipment surfaces.
Rethinking “clean” in the age of biofilm
The presence of biofilm on healthcare surfaces changes the basic question from “Did we wipe the surface?” to “Did we disrupt and remove the attached community?” Traditional testing methods and product claims based on planktonic microbes do not always reflect real-world performance against surface-attached cells and biofilms.
Effective strategies must consider:
- Surface design and material selection that reduce microbial attachment and make biofilm formation more difficult.
- Cleaning chemistries and tools validated for their ability to break up biofilm matrix, not just kill free-floating organisms.
- Procedures that emphasize mechanical action, correct contact time, and routine disruption of high-risk biofilm reservoirs (for example, around sink areas, bed rails, and shared equipment).
Biofilm may be invisible, but its impact on environmental hygiene and patient safety is very real. By understanding how microbes attach, organize, and protect themselves on surfaces, healthcare leaders can better evaluate products, redesign processes, and work with environmental services teams to move beyond “looks clean” toward environments that are truly clean at the microscopic level.
Join us at ISSA Show North America for the Biofilm panel discussion — Biofilm: Beyond Disinfection — Breaking Through the Protective Matrix in the Healthcare Environment — Monday, November 16, 11:30 am–12:30 pm, featuring Darrel Hicks and Nancy Schlossberg.
